

Learn how ophthalmology medical billing services handle complex claims, reduce denials, manage coding challenges, and help eye care practices improve collections and cash flow.
Ophthalmology medical billing services handle coding, claims, denials, and collections for eye care practices. Outsourcing them makes sense when injections, surgeries, and payer rules outgrow your front-office team.
Eye practices rarely lose revenue in big, obvious ways. It leaks out through a missed modifier, an unreported drug waste unit, or an unappealed denial.
Few specialties pack as much into one visit. A single patient can get an exam, imaging, an injection, and a drug claim in one afternoon. Each piece has its own code, modifier, and payer rule. One small error can hold up the whole claim.
Quick answer: Ophthalmology medical billing services are outsourced teams that code, submit, and collect payment for eye care claims. Most charge a percentage of collections, often 4% to 8%. They pay off when they cut denials and speed up reimbursement for surgeries and injections. Always confirm current pricing in writing before you sign.
What Are Ophthalmology Medical Billing Services?
In plain terms, ophthalmology medical billing services turn your clinical documentation into paid claims. The billing team takes your exam notes, surgical reports, and test results. They assign CPT and ICD-10 codes, submit claims, and post payments. Then it works every denial and underpayment until the account closes.
What's Typically Included
Most vendors cover the same core tasks:
Insurance eligibility and benefits verification
Charge capture and coding review
Claim scrubbing and electronic submission
Payment posting and reconciliation
Denial management and appeals
Follow-up on aging accounts receivable (A/R)
Patient statements and payment collection
Monthly reporting on collections and denials
Ask about extras before you sign. Credentialing, prior authorization, and patient phone support are often separate line items. Some vendors skip them entirely.
Medical Insurance vs. Routine Vision Plans
Eye practices bill two different insurance systems. Medical insurance covers eye disease, injury, and surgery. Vision plans cover routine exams, glasses, and contacts. Eligibility, documentation, and payment rules differ between the two.
For example, Medicare generally excludes routine refractive exams. The refraction code, 92015, is typically the patient's responsibility. Source: aao.org
A routine visit can turn medical mid-exam. A patient with blurry vision might show signs of glaucoma. Your documentation must show that shift clearly. Otherwise, the payer denies the medical claim, or your team bills the wrong plan.

Why Is Ophthalmology Billing So Complex?
Ophthalmology mixes office visits, minor procedures, surgery, drugs, and diagnostic tests in a single day. Each one follows different coding and payer rules. That mix is why general vendors struggle to deliver strong ophthalmology medical billing services. Your biller needs to understand eye care, not just claims.
Eye Codes vs. E/M Codes
Ophthalmology has two code families for office visits. General E/M codes cover visits by complexity or time. Eye codes (92002 to 92014) cover intermediate and comprehensive eye exams.
Payer preferences vary. Some accept either family. Others push back when your choice does not match the record.
Modifiers protect your payment here:
-25: a significant, separately identifiable E/M on the same day as a procedure
-24: an unrelated E/M during a postoperative global period
-57: an E/M that led to the decision for major surgery
-RT, -LT, -50: right eye, left eye, or both eyes
Modifier errors are a frequent denial trigger. Build the rules into your claim scrubber.
Cataract Surgery Billing and the Global Period
Standard cataract surgery with an intraocular lens uses CPT 66984. Complex cases use 66982. Both carry a 90-day global period.
The global period bundles routine follow-up care into the surgery payment. You cannot bill a normal postoperative visit separately. An unrelated problem, however, may qualify for modifier -24.
Co-management adds another layer. When an optometrist handles aftercare, the surgeon bills with modifier -54 (surgical care only). The optometrist bills with -55 (postoperative care only). Both need a documented transfer of care and matching dates. Payers deny overlapping claims quickly. Source: cms.gov/global-surgery
Intravitreal Injection and Drug Billing
Injections often generate the highest revenue per visit in a retina practice. They also carry the most billing risk.
A typical claim needs the injection code (67028), the drug's J-code, drug units, laterality, and a supporting diagnosis. Each anti-VEGF drug has its own code. Aflibercept uses J0178, ranibizumab uses J2778, and faricimab uses J2777. Biosimilars have separate codes too.
For example, a 2 mg aflibercept dose in the right eye bills as 67028-RT plus J0178 for two units. Confirm each payer's laterality and unit rules.
Four pitfalls cost practices the most money:
Wrong units: The dose and the billed units do not match.
Waste reporting: Medicare requires JW for discarded drug amounts and JZ when nothing was discarded.
Missing prior authorization: This is common with Medicare Advantage plans.
Step therapy: The payer requires a lower-cost drug first.
Buy-and-bill also strains cash flow. You purchase the drug first and get paid later. Track that gap closely.
Diagnostic Testing and Medical Necessity
Retinal OCT (92134), optic nerve OCT (92133), visual fields (92081 to 92083), and fundus photography (92250) draw payer scrutiny. Reviewers check whether the test changed patient care.
Link each test to a diagnosis that supports it. Document why you ordered it and what you found. Keep a signed interpretation and report in the chart. Many payers also limit how often you can repeat a test. Bill more often than allowed, and the claim is denied.
Premium IOLs and Patient-Pay Workflows
Medicare covers a conventional lens. Patients who choose a premium lens or astigmatism correction pay the added cost. CMS Ruling 05-01 addresses how practices may charge for those extras. Your team must separate covered and noncovered charges. Source: cms.gov/ruling-05-01
Chasing balances after surgery is usually slower and less successful. Collect upfront whenever you can. Build a simple workflow:
Present lens options and pricing before surgery day.
Get a signed financial acknowledgment.
Collect the patient's portion in advance.
Bill covered and noncovered portions separately.
Common Ophthalmology Claim Denials and How to Prevent Them
Denial reason | Typical cause | Prevention step |
Modifier error | Missing -25, -24, or laterality | Add modifier rules to your claim scrubber |
Medical necessity | Diagnosis does not support the test | Link a specific diagnosis and document findings |
Missing prior authorization | Injection or surgery not approved | Verify requirements at scheduling |
Global period conflict | Routine postoperative visit billed separately | Flag patients inside the 90-day window |
Wrong plan billed | Medical and vision coverage confused | Verify both coverages at check-in |
Drug unit or waste error | Vial size and dose mismatch | Reconcile drug logs against claims |
Track denials by reason every month. Patterns point to fixable front-end problems. A good vendor shares this data without being asked.
How Much Do Ophthalmology Medical Billing Services Cost?
Most companies charge a percentage of collections. Common quotes run from about 4% to 8%, depending on practice size, complexity, and services included. Treat those figures as ballpark numbers and get written quotes.
Pricing Models: Percentage, Flat Fee, Per-Claim, and Hybrid
Percentage of collections: The vendor earns only when you get paid. This is the most common model.
Flat monthly fee: Costs are predictable. The vendor has less incentive to chase old claims.
Per-claim fee: This suits low volume. Costs climb fast as claims grow.
Hybrid: A smaller base fee plus a lower percentage. It balances predictability and incentive.
Hidden Fees to Watch For
Setup or onboarding charges
Clearinghouse fees
Statement printing and mailing costs
Credentialing or prior authorization add-ons
Minimum monthly charges
Fees for cleaning up old A/R
Worked Example
Here is a hypothetical example, not a quote. Assume a practice collects $100,000 per month and compares two options.
Item | In-house | Outsourced (6% fee) |
Monthly collections | $100,000 | $100,000 |
Two billers (salary plus 25% benefits) | $9,375 | $0 |
Software and clearinghouse | $800 | Included |
Vendor fee | $0 | $6,000 |
Total monthly billing cost | $10,175 | $6,000 |
Cost as share of collections | 10.2% | 6.0% |
Outsourcing wins on paper here. But the bigger variable is whether the vendor collects more than your team does. Compare net collections, not fees alone.
How to Choose Ophthalmology Medical Billing Services
Comparing ophthalmology medical billing services is easier with a scorecard. Score each vendor on the questions and red flags below.
Questions to Ask Before You Sign
Are your coders credentialed, such as CPC, and experienced in ophthalmology?
Which EHR and practice management systems do you work in?
How do you handle prior authorization for injections?
What is your clean claim rate for ophthalmology clients?
How quickly do you work denials?
What reports will I receive, and how often?
Who is my dedicated point of contact?
Can I speak with two ophthalmology references?
Red Flags
Absolute promises. One vendor claims it has raised reimbursements for every practice it serves and guarantees higher revenue. No honest biller controls payer behavior.
No named references
Refusal to share sample reports
Long lock-in periods with steep exit fees
Vague answers about who owns your data and payer accounts
Contract Terms That Matter
Termination: Look for 30 to 90 days' notice without penalty.
Data ownership: Your records and payer relationships stay yours.
Transition help: The vendor returns your data in usable form.
Fee definitions: Know exactly what counts as "collections."
Compliance: Sign a HIPAA business associate agreement before granting access.

Not sure if your current billing is costing you revenue? Get a free billing audit from MI MedCare.
KPIs to Track After You Outsource
Review these numbers monthly once ophthalmology medical billing services go live.
KPI | Common target | Why it matters |
Clean claim rate | 95% or higher | Shows front-end coding quality |
Denial rate | 5% or lower | Flags recurring errors |
Days in A/R | 30 to 40 | Measures payment speed |
Net collection rate | 95% or higher | Shows how much collectible revenue you capture |
Injection payment lag | Track and trend | Protects cash flow on drug spend |
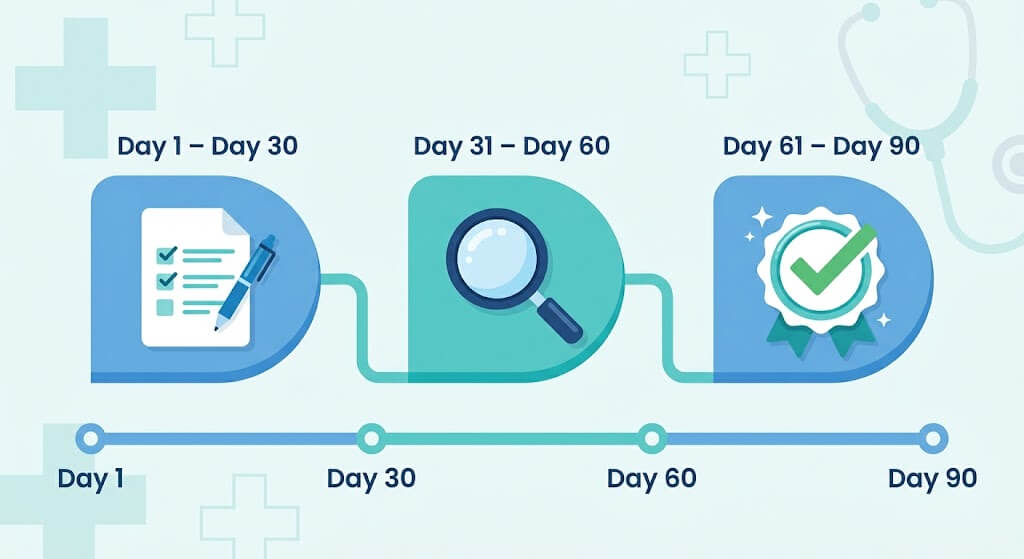
What Onboarding Looks Like: The First 90 Days
Onboarding for ophthalmology medical billing services often takes about 90 days.
Days 1 to 30: Sign the business associate agreement and grant system access. Audit open A/R, map workflows, and verify payer enrollments.
Days 31 to 60: Clear the backlog and work aging claims. Fix the top denial causes and start regular reporting.
Days 61 to 90: Review KPIs and tune scrubber rules. Train providers and staff on documentation gaps.
Regulatory and Payer Changes in 2026
Rules change every year, so treat this as a watch list rather than a fixed reference.
Medicare Physician Fee Schedule updates
MIPS quality reporting requirements
Payer policies on anti-VEGF drugs, including biosimilar preferences
Prior authorization rules for Medicare Advantage plans
New or revised CPT and HCPCS codes
Billing Considerations by Subspecialty
Subspecialty | Biggest billing risk |
Retina | Drug units, waste reporting, prior authorization |
Glaucoma | Testing frequency and medical necessity |
Cornea | Procedure coding accuracy and laterality |
Oculoplastics | Medical vs. cosmetic determination for eyelid surgery |
Pediatric | Age-specific screening rules and strabismus coding |
Refractive | Cash-pay collections and pricing transparency |
How much do ophthalmology medical billing services cost?
Most charge 4% to 8% of collections. Flat-fee, per-claim, and hybrid models also exist. Ask about setup fees, clearinghouse costs, and minimums. Compare the total against your current in-house spending.
Can a small practice benefit from outsourcing?
Yes. Small teams often lack coding depth for injections and surgery. Outsourcing also removes the risk of one biller leaving. Run the numbers using your own collections.
What is the difference between medical and vision insurance billing?
Medical plans pay for eye disease, injury, and surgery. Vision plans pay for routine exams and eyewear. Each has different eligibility, documentation, and coding rules.
Why are ophthalmology claims denied so often?
Common causes include modifier errors, weak medical necessity documentation, missing prior authorization, and global period conflicts. Most are preventable at scheduling and charge entry.
Do billing companies work with my EHR?
Most vendors work inside common EHR and practice management platforms. Confirm yours by name. Ask for a reference practice using the same system.
How long does it take to switch billing companies?
Plan on 60 to 90 days to stabilize. Payments may slow briefly during the handoff.
Key takeaways:
Ophthalmology billing is complex because visits, drugs, surgery, and testing overlap.
Injections and cataract surgery carry the highest denial risk.
Compare vendors on net collections, not just fee percentages.
Track clean claim rate, denial rate, and days in A/R monthly.
Related Posts

Oncology Billing Services: How They Work, What The Cost Is, and How to Choose the Right Partner in 2026

What Are Community Rehabilitation Companies? A Complete US Guide to Types, Funding & Billing

Gastroenterology Billing Services: Coding Accuracy, Denial Prevention, and Payer Rules That Affect Reimbursement
Comments (0)
Comments are disabled for this post.